


Tardive dystonia isn’t a variation of tardive dyskinesia, it’s a separate and more severe condition. Same drug class, different mechanism: sustained, painful muscle contractions rather than repetitive orofacial movements. Antipsychotics are the usual culprit; metoclopramide is overlooked more often than it should be. Reversal is possible, but exposure duration determines the odds. The longer the drug continues after symptoms start, the narrower the window gets.
According to Dr. Gurneet Singh Sawhney, one of the best neurosurgeon in Mumbai, “Tardive dystonia is underdiagnosed because symptoms get attributed to the psychiatric condition being treated rather than the medication treating it and every month the offending drug continues, the window for full reversal narrows.”
Dystonia symptoms present for more than three months without a clear reversible cause?
Which Types of Dystonia Have the Best Chance of Resolving Without Treatment?
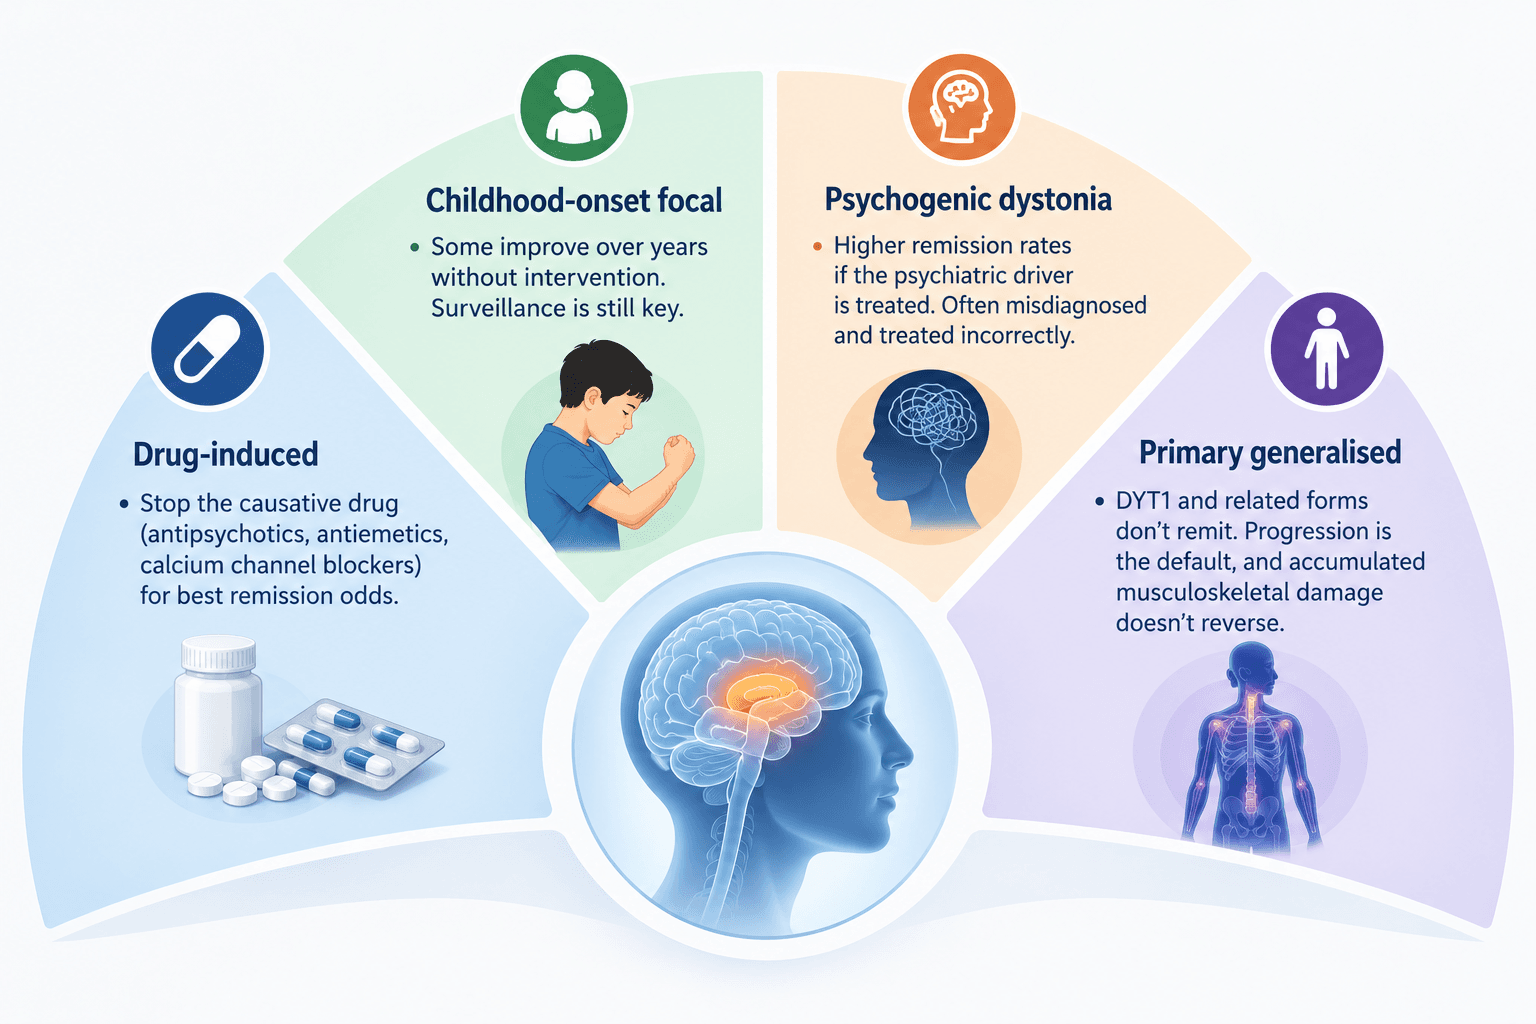
Non-remitting cases go straight into the functional neurosurgery assessment pathway there’s no benefit in watching further.
When Does Dystonia Require Treatment Rather Than Observation
Three months without spontaneous improvement is the threshold. Not a hard rule, but a practical one.
Pain and function: Botulinum toxin is safe enough that there’s no good reason to defer it when dystonia is already disrupting sleep, producing sustained pain, or limiting daily function — and the functional losses that accumulate during delay aren’t recovered once treatment eventually starts.
Fixed postures: This is the part patients don’t expect. Untreated dystonia causes joint contractures and muscle hypertrophy that persist after the neurological problem is addressed so delayed treatment creates a second layer of disability that’s harder to reverse than the original movement disorder ever was.
Spread risk: Focal dystonia doesn’t always stay focal. Cervical dystonia spreads to the shoulder and arm in a meaningful proportion of patients, and there’s no evidence that waiting reduces that risk quite the opposite.
Surgical candidacy: Patients heading toward DBS surgery do better when they arrive before severe fixed deformities have developed; pallidal stimulation works on the neurological circuit, not the musculoskeletal changes sitting on top of it.
Observation only makes sense when a reversible cause is actively being addressed; everything else needs a specialist referral, not a wait. Patients with suspected cervical dystonia, the most common focal type, should seek specialist review early given the condition-specific remission rates achievable with the right treatment.
Why Choose Dr. Gurneet Singh Sawhney?
Dr. Gurneet Singh Sawhney holds MBBS, MS (General Surgery), and MCh (Neurosurgery), ranking first in the MCh university examination with fellowship training in Functional Neurosurgery under Prof. Taira at Tokyo Women’s Medical University and Epilepsy Surgery under Prof. Sugano at Juntendo University, Japan, with dedicated expertise in DBS for dystonia, botulinum toxin management, stereotactic thalamotomy, and pallidotomy across focal and generalised dystonia presentations.
His dystonia assessments identify the cause and type before any treatment pathway is recommended because the remission question can only be answered once the dystonia type is confirmed, not before.
Frequently Asked Questions
Can focal dystonia like cervical dystonia go away without treatment?
Less than twenty percent of cervical dystonia patients achieve spontaneous remission, and most relapse.
Does childhood dystonia have a better chance of resolving spontaneously?
Some paediatric focal dystonias improve over time, but primary generalised dystonia in children doesn’t remit spontaneously.
If dystonia goes away, can it come back?
Yes, relapse after spontaneous remission is common, particularly in focal dystonias where remission rates are already low.
How long should dystonia be present before starting treatment?
Most specialist centres initiate treatment after three months of persistent symptoms without spontaneous improvement.
Disclaimer: The information shared in this content is for educational purposes only and not for promotional use.