


Usually, no. One brief tonic-clonic seizure that stops on its own within two minutes does not leave structural injury on MRI, and follow-up studies do not detect a lasting cognitive deficit afterwards. That is the reassurance most patients are looking for, and for most people it holds. But it is not the complete answer. Status epilepticus is different. So is a decade of uncontrolled epilepsy. Duration, frequency, and how fast treatment arrives are what actually determine whether a seizure leaves a mark or does not.
Brief focal seizures and typical absence seizures sit in the same low-risk group. The concern begins when seizure activity is prolonged, repeated in quick succession, or allowed to continue untreated for years. That distinction, between a short self-terminating event and sustained electrical activity, is the one that matters most for the brain.
According to Dr. Gurneet Singh Sawhney, Neurosurgeon in Mumbai,
“A single brief seizure rarely causes lasting damage, but status epilepticus beyond 30 minutes is a neurological emergency, and every minute of untreated convulsive status increases the probability of permanent hippocampal injury.”
Seizures recurring despite medication, or lasting longer than five minutes without stopping? Get your seizure control reviewed before damage accumulates.
What Types of Seizures Carry the Highest Risk of Brain Damage
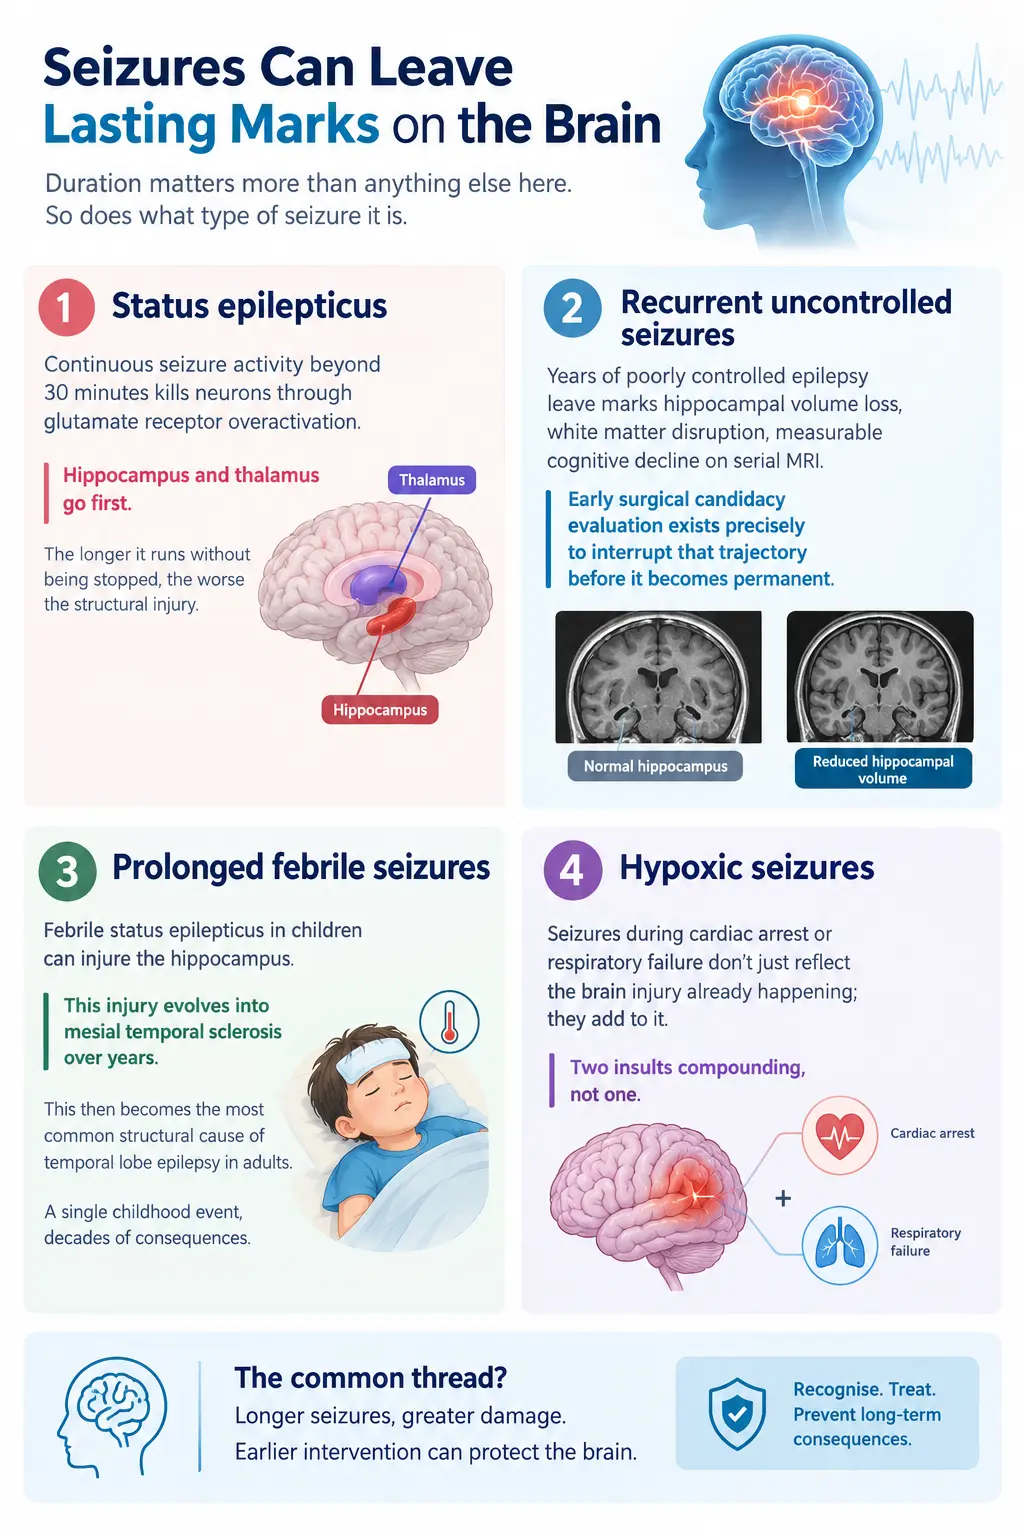
Brief focal seizures, typical absence seizures, and tonic-clonic seizures that stop within two minutes do not produce structural injury. The concern is prolonged, repeated, or status-level activity. That is the line.
- Status epilepticus: Continuous or repeated seizure activity without recovery in between. This carries the highest risk and is treated as a medical emergency.
- Recurrent uncontrolled seizures: Years of poorly controlled epilepsy, rather than any single event, drive the cumulative changes seen on imaging.
- Prolonged febrile seizures: Febrile seizures in children are usually brief and harmless, but unusually long ones warrant assessment.
- Hypoxic seizures: Where the seizure occurs alongside reduced oxygen supply, the injury risk comes from the hypoxia as much as the seizure itself.
- Brief, self-terminating seizures: Focal, absence, and short tonic-clonic seizures. No structural injury is expected.
This is exactly what epilepsy surgery candidacy evaluation aims to prevent, by bringing seizures under control before cumulative injury sets in.
What Brain Changes Do Recurrent Seizures Produce Over Time
Chronic epilepsy does not leave the brain unchanged. The changes simply do not show up on a standard scan, or on a standard cognitive test, until years in.
- Hippocampal sclerosis: Limbic seizures affect hippocampal neurons steadily rather than dramatically. The sclerosis seen on MRI in long-standing temporal lobe epilepsy is not only a cause of seizures; it is also something the seizures help produce. It works in both directions, and that is the problem.
- Cognitive decline: Memory and processing speed drop in patients with decades of uncontrolled generalised epilepsy. Medication side effects are part of it. But the seizures themselves disrupt learning and consolidation networks every time they fire, and that disruption compounds.
- White matter changes: Diffusion tensor imaging finds tract disruption well beyond the seizure focus. This network-level change from propagating activity is not focal and is not visible on standard MRI, but it is there, and it tracks with cognitive and psychiatric outcomes more closely than lesion size does.
- Psychiatric comorbidity: Depression, anxiety, and psychosis are all more common in epilepsy than in the general population. Shared neurobiological mechanisms in limbic and frontal networks explain part of it, which is why functional neurosurgery maps these networks before any resection; they are already under strain.
None of this is inevitable. It accumulates when seizures stay uncontrolled. Stop the seizures, and you stop the accumulation. For what happens in the brain immediately after a seizure and how recovery unfolds, see brain recovery after seizure.
How Is Seizure-Related Brain Damage Prevented and Treated
The earlier seizures are controlled, by whatever means fits the seizure type, the less damage accumulates. Waiting is not neutral. It is the time during which the injury is occurring.
- Treat prolonged seizures as an emergency: A seizure lasting beyond five minutes, or repeated seizures without recovery in between, needs emergency care rather than watchful waiting.
- Review medication when seizures persist: If seizures continue despite appropriately trialled medication, the treatment plan needs reassessment rather than repetition.
- Investigate properly: EEG monitoring and an epilepsy-protocol MRI help identify the seizure focus and assess hippocampal volume.
- Consider surgical evaluation early: In drug-resistant epilepsy, candidacy assessment for epilepsy surgery is about stopping the accumulation, not just managing symptoms.
For a closer look at what drives multiple seizures in a single day, see What Causes Multiple Seizures in a Day.
Epilepsy that has not responded to medication deserves a second look. Discuss EEG, imaging, and surgical candidacy with a specialist.
This article is for general patient education and does not replace advice from your treating doctor.